Neurotechnology and human augmentation
Interfaces between nervous systems and machines.
Technology profiles

Accelerated transcranial magnetic stimulation
Accelerated transcranial magnetic stimulation (TMS) gives many short sessions over about five days, and some versions target each person's brain network using a brain scan. The FDA cleared one such system, SAINT, in 2022, but most of the evidence comes from small trials and it is not yet clear how long the benefit lasts.
Adaptive deep brain stimulation
Deep brain stimulation (DBS) uses implanted electrodes to deliver electrical pulses to deep brain areas and is established for Parkinson's disease and other movement disorders. Adaptive DBS reads a brain signal and changes stimulation as that signal changes; the FDA approved a Medtronic adaptive system for Parkinson's disease in early 2025, according to the manufacturer, while its use in depression remains experimental.
Bionic limbs with nerve and bone connection
Artificial arms and legs are being attached directly to bone and linked to the wearer's nerves and muscles, so they can be controlled more naturally and, in early studies, give some sense of touch. A bone-anchored system is approved in the US for some above-knee amputees, while nerve and muscle interfaces are still tested in small studies.
Brain organoids
Brain organoids are small three-dimensional clumps of brain-like tissue grown from human stem cells. They are used to model brain development and disease, and some have been transplanted into rat brains, but they remain small, lack blood vessels and do not yet show the learning that 'organoid intelligence' proposals describe.
Brain-computer interfaces
Brain-computer interfaces read electrical activity from the brain and turn it into text, speech or device commands. Research teams have decoded attempted speech from implanted electrodes, and one company has tested an implant placed through blood vessels. A September 2026 study used electrodes on the brain's surface to control a virtual avatar in two of three people with paralysis. Only a small number of people have been studied in all of this work.
Closed-loop brain stimulation for epilepsy
Some implanted devices detect programmed patterns of brain activity and respond with a short pulse of electrical stimulation. The NeuroPace RNS System was approved by the US Food and Drug Administration in November 2013. Long-term studies show seizure reductions on average, but results vary widely, and the device does not stop seizures in everyone. Most of the evidence comes from studies sponsored by the device maker.
Cochlear implants
Cochlear implants are electronic devices that stimulate the auditory nerve to give a sense of sound to people with profound deafness or severe hearing loss. About 736,900 devices had been implanted worldwide by December 2019, but results vary between people and hearing in noise and music remains difficult.
Consumer brain-sensing wearables
Headbands and earbuds sold to consumers record brain signals to estimate sleep stages. Small studies show that some of these devices agree reasonably well with lab sleep scoring for the main stages, but evidence for light sleep, clinical groups and long-term home use is thin, and some jurisdictions now treat neural data as sensitive.
Cryonics
Postmortem preservation with the hope of future revival. No human revival has been demonstrated. A detailed article separates that speculative goal from demonstrated organ and neural-tissue research, including results published in 2025 and 2026.
Focused ultrasound for the brain
Focused ultrasound sends sound waves through the skull to a small target in the brain. A high-intensity version is approved to destroy tissue for essential tremor, while low-intensity versions that change brain activity are still in early human research.
High-density neural probes
High-density neural probes are thin silicon shanks with hundreds or thousands of recording sites, such as Neuropixels, that record many individual neurons at once. In mice and rats they have followed the same neurons for more than two months, while in people they have so far been used mainly during brain surgery, where recording yield and probe durability remain limits.
Optogenetics
Optogenetics uses light-sensitive proteins, introduced into cells by genetic modification, to switch those cells on or off with light. It began as a laboratory tool for controlling neurons, and its human use so far is early-stage, including a single-patient report of partial vision recovery in 2021.
Peripheral nerve interfaces
Electrodes placed on or in nerves outside the brain and spinal cord can pick up a person's movement signals to control a prosthetic limb, and can send electrical pulses that the nerve reads as touch or pressure. Human studies so far are small, with one to four participants each, and the sources reviewed here do not report an approved nerve interface device.
Retinal prostheses and vision restoration
Retinal prostheses are implants that use electrodes or light-sensitive chips to stimulate the remaining retina in people who have lost their light-sensing cells. The Argus II was approved by the FDA in 2013 for advanced retinitis pigmentosa, and its production was suspended in 2019, while the PRIMA implant improved central vision for most participants assessed in a 2025 trial in geographic atrophy.
Sleep neurostimulation
Sleep neurostimulation plays sounds or passes weak electrical currents into the brain, timed to the slow waves of deep sleep, to try to strengthen those waves and possibly memory. Small studies report stronger slow waves and spindles, but memory benefits have not replicated reliably, and consumer headbands have little independent testing.
Spinal cord stimulation for paralysis
Electrical stimulation of the spinal cord can help some people with spinal cord injury move again. Implanted epidural systems have restored walking and trunk control in very small research cohorts. A non-invasive system called ARCEX was studied in a 65-person trial, and its maker states that it is FDA cleared to improve hand sensation and strength in people with incomplete cervical spinal cord injuries.
Vagus nerve stimulation
Vagus nerve stimulation sends small electrical pulses to the vagus nerve, a long nerve linking the brain with the heart, lungs and gut. Implanted systems are FDA-approved for epilepsy and for arm rehabilitation after stroke, but the evidence for depression and for rheumatoid arthritis is much less settled.
How far away are we?
Artificial limbs that move and feel like real ones
Pilots · 7 of 10 steps done
Better deep sleep on demand
Pilots · 9 of 12 steps done
Brain data protected by law
Pilots · 5 of 9 steps done
Brain implants that stop seizures before they spread
Scaling up · 5 of 8 steps done
Brain-computer interfaces for everyday use
Pilots · 4 of 8 steps done
Giving people back their voice with brain implants
Engineering prototypes · 4 of 6 steps done
Restoring sight to blind people
Pilots · 4 of 8 steps done
Treating illness through the vagus nerve
Pilots · 6 of 8 steps done
Treating severe depression in days with brain stimulation
Pilots · 7 of 9 steps done
Walking again after spinal cord injury
Engineering prototypes · 4 of 6 steps done
Breakthroughs
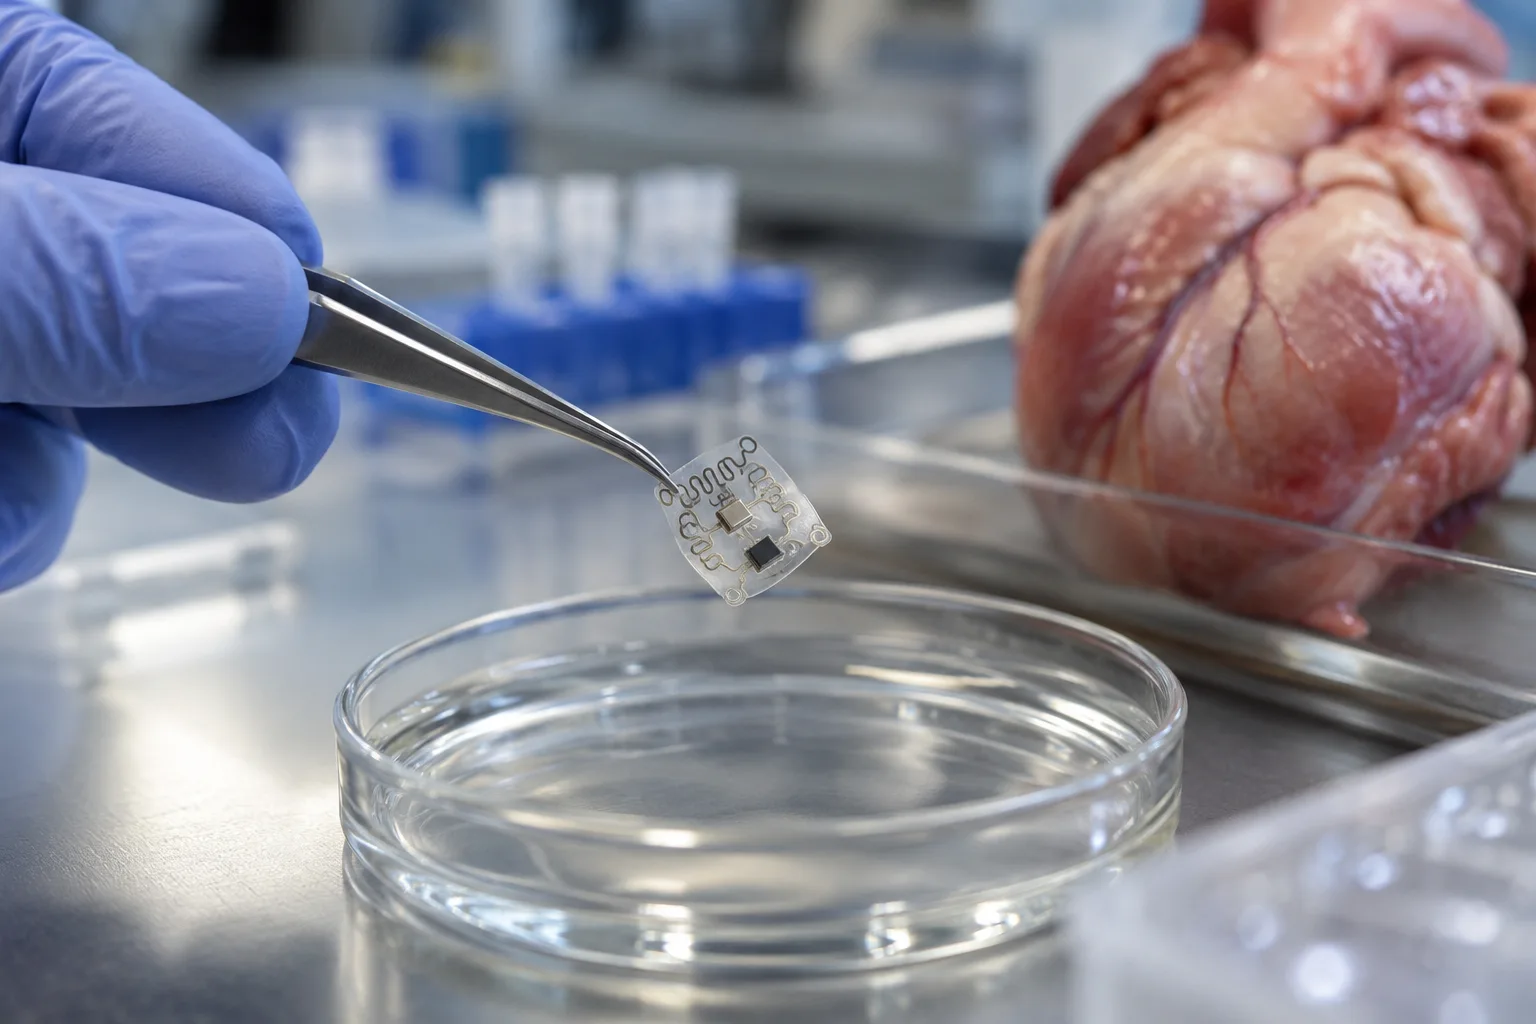
Bioresorbable metal-free magnet enables untethered organ monitoring in porcine models
Researchers report a graphitic-carbon-nitride-derived metal-free molecular magnet integrated into catheter-deliverable epicardial patches and injectable hydrogels, coupled to a skin-interfaced Hall sensor array. In porcine models, the system continuously assessed cardiac ejection fraction for four weeks before the material underwent reported benign bioresorption. The abstract does not state the number of animals or detailed protocol.
Brain implant decodes speech and gestures together in two people with paralysis
In a study of three participants with severe speech and movement impairment, a 253-channel electrocorticography (ECoG) array implanted on the pial surface of the left hemisphere, over areas of speech production and motor movement, was used for real-time decoding. Two participants (Bravo-1r and Bravo-6) completed the simultaneous speech and gesture avatar tasks; the third withdrew before that stage. In a cued conversation task with a restricted set of phrases and gestures, Bravo-6 reached 75.0% speech accuracy (95% CI 55.0 to 90.0) and 85.0% gesture accuracy (95% CI 70.0 to 100.0) over five blocks. Bravo-1r, with five phrases and four gestures, reached a median of 100% for both over three blocks. In a copy task with ten phrases and ten gestures, Bravo-6 scored 70.0% for speech and 66.0% for gestures, against chance levels of 9.1% each.
Implanted vagus nerve device shows higher 3-month response than sham in rheumatoid arthritis trial
In RESET-RA, a double-blind, sham-controlled trial of 242 adults with rheumatoid arthritis who had an inadequate response to, or intolerance of, biologic or targeted synthetic DMARDs, an implanted device acting on the vagus nerve gave an ACR20 response at 3 months of 35.2% with active stimulation, against 24.2% with sham (P = 0.0209). The primary endpoint was the 3-month ACR20 response. Open-label follow-up, which had no control group, reported ACR20 responses of 50.0% at 6 months and 52.8% at 12 months (all completers). Related serious adverse events occurred in 1.6% of patients, all perioperative and resolved.
PRIMA subretinal photovoltaic implant improves central vision acuity in geographic atrophy at 12 months
In an open-label, multicentre, single-group study with a baseline comparison, 38 adults with geographic atrophy secondary to age-related macular degeneration received a PRIMA subretinal photovoltaic implant used with near-infrared-projecting glasses. Vision was assessed with and without the glasses at 6 and 12 months. Of the 32 participants assessed at 12 months, 26 (81%) reached a clinically meaningful visual acuity gain of at least 0.2 logMAR from baseline. Multiple imputation across all 38 participants estimated 80%. The authors report 26 serious adverse events in 19 participants, most of them within two months after surgery.
Adaptive deep brain stimulation for Parkinson's tested over months in a small open-label trial
In the ADAPT-PD trial, 68 people with Parkinson's disease who already used conventional deep brain stimulation (cDBS) were enrolled. Of these, 40 were evaluated on dual-threshold adaptive DBS (DT-aDBS) and 35 on single-threshold adaptive DBS (ST-aDBS). The primary outcome was on-time without troublesome dyskinesia. Under the prespecified threshold, 95% (DT-aDBS) and 87% (ST-aDBS) of evaluated participants met the goal. The threshold was revised after the planned analysis to a post hoc limit of no more than 2 hours a day of lost on-time without troublesome dyskinesia. Under that revised threshold, 91% (DT-aDBS) and 79% (ST-aDBS) met it. Total electrical energy delivered (TEED), a secondary outcome, was about 13% lower with DT-aDBS (borderline, P = .05) and about 15% lower with ST-aDBS (P = .01) than with cDBS. Mean aDBS exposure was 17.5 months (range 3 to 27). The authors report no unanticipated serious adverse device events.
Brain-computer interface synthesises a participant's voice in real time, including intonation
Using 256 microelectrodes implanted in the ventral precentral gyrus of one man with ALS and severe dysarthria, the team decoded neural activity directly into synthesised voice with closed-loop audio feedback, rather than into text. The decoder also captured paralinguistic features, letting the participant change intonation and sing short melodies through the system.
Low-intensity focused ultrasound to the amygdala changes brain activity and reduces distress symptoms in an early human study
In a double-blind, within-subject, sham-controlled target engagement study, MRI-guided low-intensity transcranial focused ultrasound was aimed at the left amygdala during fMRI in 29 patients with mood, anxiety or trauma-related disorders and 23 healthy comparison subjects. Active stimulation reduced left amygdala BOLD signal on average compared with sham. The same patients then received 15 daily sessions over three weeks in an unblinded single-arm trial. The primary outcome, the General Distress subscale of the Mood and Anxiety Symptom Questionnaire, fell significantly (p = 0.001, Cohen's d = 0.77). The authors report no serious adverse events.
Ten people with chronic spinal cord injury show gains in strength and balance over one year
The operator's announcement reports that, in a one-year study of 10 adults with chronic cervical or thoracic spinal cord injury, 120 treatment sessions of transcutaneous spinal cord stimulation (ONWARD's ARC-EX Therapy), combined with activity-based rehabilitation, were followed by gains in upper body strength, trunk control and balance. The announcement says there was no indication of a plateau in benefit after one year. It reports that three participants improved their AIS classification, and four showed a change in neurological level of injury, including one who moved from complete to incomplete injury. The announcement gives no numerical strength, balance or function scores and no adverse event data.
Intracortical speech neuroprosthesis reaches 97.5% accuracy in a man with ALS
In one 45-year-old man with ALS and severe dysarthria, four microelectrode arrays (256 electrodes) were implanted in the left precentral gyrus as part of the BrainGate2 trial. On the first day of use, after 30 minutes of calibration data, decoding reached 99.6% word accuracy on a 50-word vocabulary. On day two, after 1.4 more hours of training, it reached 90.2% on a 125,000-word vocabulary. With further training it sustained 97.5% accuracy in self-paced conversation over 248 cumulative hours across 8.4 months.
Focused ultrasound to left prefrontal cortex eased depression scores versus sham in small trial
In a randomised, double-blind, sham-controlled trial in patients with major depressive disorder, low-intensity transcranial focused ultrasound (250 kHz, NS-US100 device) was aimed at the left dorsolateral prefrontal cortex over six sessions in two weeks. Of 26 randomised participants, 23 completed (11 active, 12 sham). On the Montgomery-Åsberg Depression Rating Scale (MADRS), the group-by-session interaction was significant (F(1,21) = 9.0, p = 0.003). At follow-up, mean MADRS scores were 14.8 ± 7.2 with active stimulation and 24.8 ± 9.3 with sham. The response rate (at least a 50% fall in MADRS) was 54.5% (6 of 11) with active stimulation and 8.3% (1 of 12) with sham (p = 0.027). Remission (MADRS below 9) did not differ significantly (18.2% vs 8.3%, p = 0.590). The main effect of group across sessions was not significant (p = 0.052). The authors report that participants tolerated the sessions well without any undesired effects.